From biomarker to practice: policy pathways for the glucose ketone index in personalized nutrition

Corinne Bush
Chief Executive Officer, American Nutrition Association, United States

Amy Smith
Senior Director of Nutrition Programs & Advocacy, American Nutrition Association, United States
The glucose ketone index (GKI) and other evidence-based biomarkers have an important role in personalized nutrition care in the management of chronic diseases. However, realizing their potential requires policy changes to ensure equitable access to personalized nutrition care via competency-based education and licensure and reimbursement reform—argue Corinne Bush and Amy Smith of the American Nutrition Association.
Published on July 14th, 2026
Introduction: a system under strain—and an opportunity
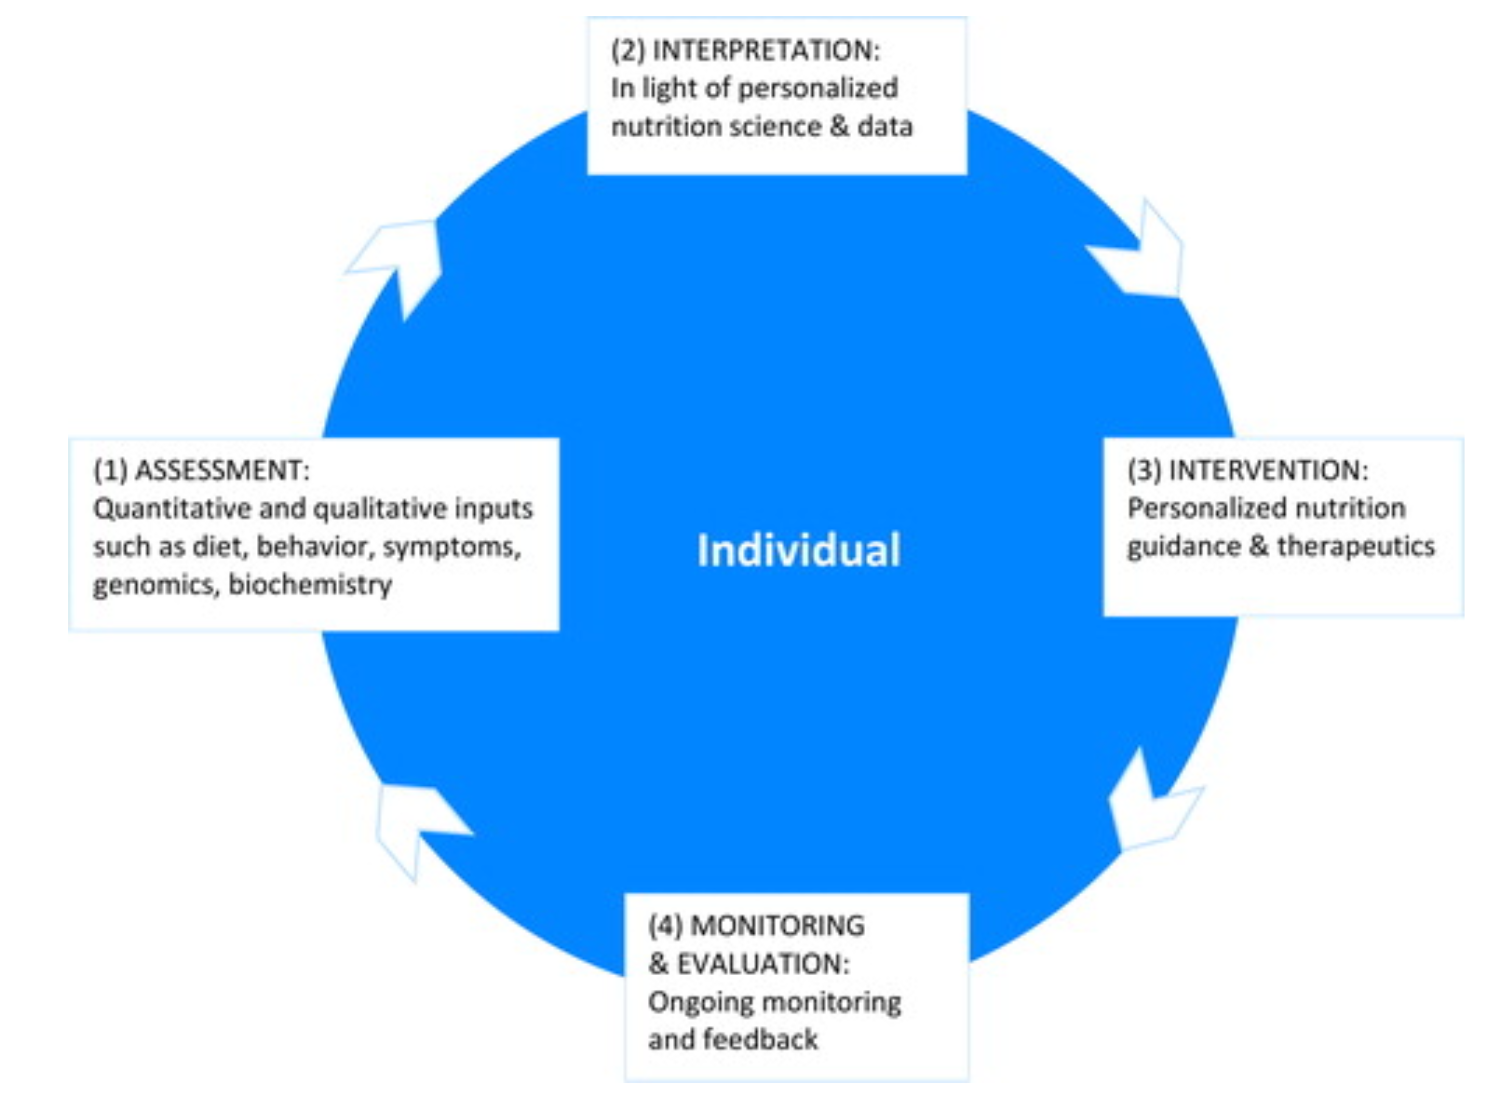
Chronic disease continues to be the leading driver of mortality and healthcare costs in America and around the world. Eight in 10 midlife adults in the United States have one or more chronic conditions and there has been a steady decline in healthspan even as lifespan increases (1). Despite advances in the science of pharmacotherapy and diagnostic tools, the healthcare system is ill-equipped to manage chronic diseases, which are often rooted in metabolic dysfunction and diet. This points to a needed fundamental shift toward personalized nutrition (PN)—a field that leverages human individuality to drive nutrition strategies that prevent, manage, and treat disease and optimize health (Figure 1) (2). PN is based on the knowledge that what is effective for one person may not be effective for another. Genetics, family history, environment, residence, medications, and other factors all play crucial roles in determining optimal nutrition care, and indeed “whole-body” care.
Actionable, evidence-based biomarkers, including the glucose ketone index (GKI) described in a Frontiers in Science lead article by Lee et al. (3) and other metabolic indicators such as the homeostatic model assessment of insulin resistance (HOMA-IR), triglyceride glucose (TyG) index, and triglyceride:high-density lipoprotein cholesterol (TG:HDL-C) ratio (4,5,6) have an important role in PN care. Realizing the full potential of these tools will require stronger policy and practice frameworks that support integration into healthcare delivery alongside a credentialed workforce equipped to interpret metabolic data and deliver PN protocols. Building competency across healthcare professions and expanding access to qualified nutrition professionals is essential to translating innovation into meaningful clinical practice.
The policy gap: barriers to integration
The barriers to incorporating metabolic markers such as the GKI into standard care are both systemic and structural. Clinician adoption will stay low, and practice application will remain inconsistent, until they are addressed.
PN serves as both a foundational care model and a profession in its own right. Unfortunately, there is both a shortage of foundational PN training across healthcare and a regulatory environment that prevents qualified PN professionals from practicing at the level their training supports in many states.
Healthcare education represents a systemic barrier. Medical and nursing training includes only a few hours of nutrition education across the entire training program (7, 8). Interpreting the data of a dynamic metabolic index such as the GKI requires an understanding of complex concepts, including ketogenesis, drug interactions, and the behavioral dimensions of dietary change. Nutrition education within the healthcare landscape has been on a rapid decline for years with 75% of United States medical schools not requiring any clinical nutrition courses. Fewer than 15% of practicing healthcare providers report feeling comfortable talking about nutrition with their patients (8). This lack of education indicates that physicians and other health professionals are ill-equipped to understand and treat metabolic dysfunction and disease that may be uncovered and managed by biomarker assessment such as the GKI.
Qualified nutrition professionals face further barriers resulting from the patchwork of nutrition licensure laws, at least in the United States. Some states have open practice environments. Others have restrictive laws that limit who can legally deliver clinical nutrition services, under what conditions, and to whom. In many jurisdictions, those restrictions do not reflect current credentialing standards or the actual competencies of the professionals they govern. The result is a system where a practitioner's legal scope of practice is determined less by what they know than by where they happen to live and by which credentialing pathways were historically incorporated into state law.
When qualified nutrition professionals are prohibited from delivering biomarker-informed care, patients with complex metabolic conditions either receive no nutrition care or generic guidance from providers not trained to interpret metabolic data. Neither outcome is clinically sound.
Advanced credentialing pathways, including those leading to the Certified Nutrition Specialist (CNS) credential worldwide, represent rigorous standards of training and examination, while only 24 states grant eligibility for licensure for CNSs directly. The gap between credential rigor and legal recognition of the training received is a policy failure, not a reflection of professional competence. To close this gap, and to allow qualified practitioners to practice at their level of training, states must move toward competency-based policies and evaluate practitioners and credentials based on what they are trained to do (9).
Reimbursement polices among healthcare payers can combine these problems where they limit coverage of medical nutrition therapy (MNT) or biomarker testing specifically. For example, in the United States, MNT is undervalued in the payment structures of private insurers and Medicare/Medicaid, with biomarker-informed care placed even further outside what is commonly recognized as eligible for reimbursement
Policy pathways for responsible integration
The tools and the professionals exist to address these problems—i.e., the lack of foundational PN knowledge across the healthcare spectrum and the barriers associated with payer reimbursement and jurisdictional recognition to practice.
The clearest first step to integrate these policy changes and accelerate the acceptance and practice of using GKI and other actionable metabolic biomarkers is for professional societies to produce and adopt clinical guidance for their use. Guidance should include appropriate use cases, relevant ranges for index values according to clinical contexts, thresholds for clinical review, and patient populations in whom caution is required.
Next, healthcare professionals' education and certification must accelerate to meet the upcoming demand of qualified practitioners once this policy change is implemented. The policy goals of the American Nutrition Association include expanding public access to PN through embedding PN training in medical schools and across all healthcare professions, and through state and federal legislative engagement. This requires not just opening licensure pathways but building care teams that understand PN and deploy qualified nutrition professionals in roles where they can act on metabolic data.
Reimbursement reform within nutrition care is the most actionable near-term policy change that could have the highest and most immediate impact on patients. Insurance payers invested in reducing costs from chronic metabolic disease have a clear incentive to embrace actionable biomarker use in nutrition interventions therefore they should update their reimbursement policies to cover guideline-led biomarker testing without administrative barriers.
Equity must be built into any policy framework from the start. Metabolic testing, qualified providers, and allotted time with the practitioner to implement dietary changes are not evenly distributed (10). Socioeconomic and cultural challenges pose barriers to patients that cannot be overlooked. Policies that do not address access will concentrate the benefits of PN in populations that already have better health outcomes while neglecting those that could benefit most from direct nutritional care intervention (11).
The policy changes outlined here—competency-based education and licensure and reimbursement structures that reflect what qualified professionals do—are not radical. What differentiates nutrition care is not the complexity of the policy work needed; it is that the field has been slower than others to demand it. The GKI and similar tools are making that demand harder to ignore. When patients can measure their own metabolic state in real time but cannot access a qualified professional to help them interpret it, the system has failed at a basic level. Fixing that failure is a policy choice, and the mechanisms to make it are already available.
Copyright: © 2026 [Bush, Smith]. This is an open-access article distributed under the terms of the Creative Commons Attribution License (CC BY). The use, distribution or reproduction in other forums is permitted, provided the original author(s) or licensor are credited and that the original publication in Frontiers Policy Labs is cited, in accordance with accepted academic practice. No use, distribution or reproduction is permitted which does not comply with these terms.
Generative AI statement
The authors declared that generative AI was not used in the creation of this manuscript.
Organizational logo

References
Watson KB, Wiltz JL, Nhim K, Kaufmann RB, Thomas CW, Greenlund KJ. Trends in multiple chronic conditions among US adults, by life stage, Behavioral Risk Factor Surveillance System, 2013-2023. Prev Chronic Dis (2025) 22:240539. doi: 10.5888/pcd22.240539
Bush CL, Blumberg JB, El-Sohemy A, Minich DM, Ordovás JM, Reed DG, et al. Toward the definition of personalized nutrition: a proposal by the American Nutrition Association. J Am Coll Nutr (2020) 39(1):5–15. doi: 10.1080/07315724.2019.1685332
Lee D, Duraj T, Cooper ID, Maroon J, Smith K, Abdel-Hadi W, et al. The glucose ketone index: a proposed quantitative biomarker to support cancer and chronic disease prevention and management. Front Sci (2026) 4:1763395. doi: 10.3389/fsci.2026.1763395
Lee J, Kim MH, Jang JY, Oh CM. Assessment HOMA as a predictor for new onset diabetes mellitus and diabetic complications in non-diabetic adults: a KoGES prospective cohort study. Clin Diabetes Endocrinol (2023) 9(1):7. doi: 10.1186/s40842-023-00156-3
Wan H, Cao H, Ning P. Superiority of the triglyceride glucose index over the homeostasis model in predicting metabolic syndrome based on NHANES data analysis. Sci Rep (2024) 14(1):15499. doi: 10.1038/s41598-024-66692-9
Cheng L, Bian Y, Meng Z, Jin P. Association between TG/HDL-C ratio or triglyceride-glucose index and mean arterial pressure in patients with myocardial infarction. Sci Rep (2025) 15(1):37027. doi: 10.1038/s41598-025-20158-8
Krishnan S, Sytsma T, Wischmeyer PE. Addressing the urgent need for clinical nutrition education in post graduate medical training: new programs and credentialing. Adv Nutr (2024) 15(11):100321. doi: 10.1016/j.advnut.2024.100321
DuBois S, Spencer A, Nava A, Kaminski M, Gonzalez AL, Arensberg MB. Nourish the mind: the need for nutrition-focused education in nursing to improve health outcomes. J Prof Nurs (2025) 61:160–7. doi: 10.1016/j.profnurs.2025.08.002
American Nutrition Association. CNS state-by-state practice rights [online] (2025). Available at: https://www.theana.org/wp-content/uploads/2024/04/CNS-State-By-State-Practie-Rights_Updated-Dec-2025.pdf
Totz M. Expanding access to food as medicine. The Regulatory Review (2024). Available at: https://www.theregreview.org/2024/12/04/totz-expanding-access-to-food-as-medicine/
Jiao L. Social determinants of health, diet, and health outcome. Nutrients (2024) 16(21):3642. doi: 10.3390/nu16213642
Figure 1. The personalized nutrition care model, reproduced from (2) licensed under CC BY 4.0.